
Leukemia can evolve over several weeks with a blood count (CBC) that is still not very indicative. This gap between medullary proliferation and the appearance of clear biological anomalies often traps the diagnosis, even among experienced practitioners. Understanding which clinical signals precede biological anomalies changes the game for directing a patient to a hematologist before the disease becomes advanced.
Diffuse bone pain and still normal CBC: the diagnostic trap
Chronic osteoarticular pain affecting the limbs, hips, or spine can be the very first symptom of acute lymphoblastic leukemia. A study published in August 2026 in the European Journal of Radiology showed that, in children with ALL, non-localized bone pain preceded typical blood anomalies by several weeks.
In this cohort, it was the spinal MRI that suggested the diagnosis, later confirmed by the myelogram, while the CBC remained little or not indicative.
This observation is not limited to pediatrics. In adults, persistent bone pain without trauma or identified rheumatological pathology should raise suspicion of medullary infiltration. A reassuring CBC is not enough to rule out early leukemia. We recommend, in this scenario, to request an MRI of the spine or pelvis rather than relying solely on standard blood tests.
Identifying the main signs of leukemia requires going beyond the isolated reading of the CBC and integrating these early clinical signals into the reasoning.
Isolated cytopenias and leukemic symptoms: reading beyond fatigue

Chronic fatigue is the most frequently reported symptom by leukemia patients, but it is also the most non-specific. What should raise concern is the association of rest-refractory fatigue with isolated cytopenia on at least two tests spaced a few weeks apart.
Moderate anemia without iron deficiency or identified bleeding, fluctuating thrombocytopenia, or isolated neutropenia each warrant a careful blood smear. We observe that the smear is too often omitted in outpatient medicine when values remain in the low normal range. The presence of circulating blasts, even in low proportion, immediately points towards acute leukemia.
Chronic lymphoid leukemia (CLL), on the other hand, presents differently. Persistent lymphocytosis lasting beyond several months, with or without lymphadenopathy, is the usual mode of discovery. Patients often describe recurrent respiratory infections that linger in duration and intensity. Lymphocyte immunophenotyping then confirms the diagnosis without requiring a bone marrow biopsy in the majority of cases.
Skin and bleeding symptoms: underestimated warning signals
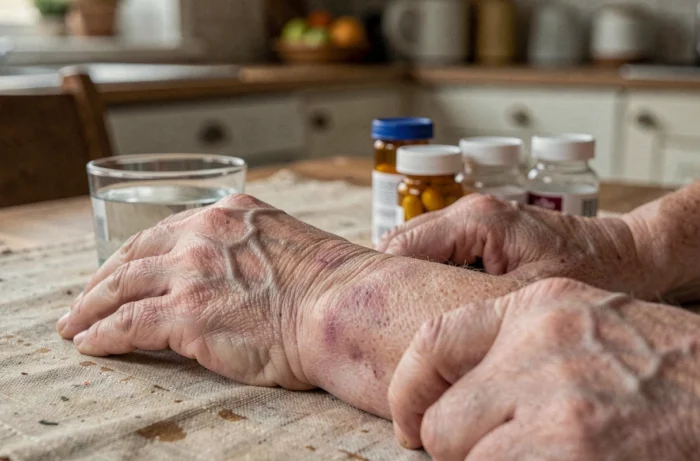
Spontaneous bruising, petechiae (small non-blanching red spots under the skin), and prolonged gum bleeding indicate thrombocytopenia or coagulopathy related to medullary infiltration. These hemorrhagic manifestations are sometimes the initial reason for consultation, even before the patient mentions fatigue.
Some skin presentations point towards specific subtypes:
- A diffuse purpura associated with DIC (disseminated intravascular coagulation) suggests acute promyelocytic leukemia (APL), which constitutes a therapeutic emergency.
- Purplish nodular skin infiltrates, called leukemides, are found in some APLs and indicate a disease that is already disseminated.
- Marked pallor, particularly of the conjunctivae and palms, indicates profound anemia due to medullary insufficiency.
The association of spontaneous bruising, fever, and fatigue should trigger an urgent blood test with a smear, without waiting several weeks for observation.
Prolonged fever and atypical infections: when to suspect leukemia
A persistent fever without an identified infectious source represents a classic mode of revelation for acute leukemias. The proliferation of blasts in the bone marrow reduces the production of functional neutrophils, exposing the patient to unusual bacterial, fungal, or viral infections.
We distinguish two clinical situations:
- Tumor fever, related to the release of pro-inflammatory cytokines by the leukemic cells themselves, without an identifiable germ.
- Infectious fever due to profound neutropenia, which can quickly evolve into sepsis if not managed.
- Profuse night sweats, frequently associated, also point towards a chronic lymphoproliferative syndrome, notably an advanced lymphoma or CLL.
An etiological assessment of prolonged fever (more than three weeks) should systematically include a CBC with blood smear and a measurement of LDH. An elevation of LDH associated with cytopenias strongly reinforces the suspicion of malignant proliferation.
Lymphadenopathy and splenomegaly: clinical examination remains crucial
Palpable, firm, painless, and non-inflammatory lymph nodes located in the cervical, axillary, or inguinal areas constitute a major warning sign in chronic leukemias. CLL is usually accompanied by diffuse lymphadenopathy at the time of diagnosis.
Splenomegaly (palpable spleen under the left costal margin) indicates sequestration of leukemic cells in the spleen. It causes a sensation of left abdominal heaviness, early satiety, and sometimes pain in the left hypochondrium. In chronic myeloid leukemia (CML), splenomegaly can be massive and constitute the primary reason for consultation.
A systematic clinical examination of lymph node areas and the spleen retains its full value. Imaging (abdominal ultrasound, CT scan) complements the evaluation but does not replace careful palpation.
The diagnosis of leukemia relies on a combination of clinical and biological signs. No isolated symptom allows for a conclusion, but their grouping, especially when it associates cytopenias, bone pain, fever, and lymphadenopathy, necessitates a rapid hematological opinion. Waiting for spontaneous normalization of an altered test remains the main cause of diagnostic delay.


